
Self-check · Emotions
Anger Management Test: how often, how big, and what it costs
Anger is not the problem — it is the emotion that registers unfairness. What makes it a problem is firing too often, too hard for the cause, lasting too long, or landing on people. These 15 questions ask about all four. Not a diagnosis.

A questionnaire, not a diagnosis. If your anger is frightening someone, that needs help now rather than a score.
-
FOUR THINGS, NOT ONEOften, big, long, costlyHow often it fires, how big it is, how long it lasts, what it costs.
-
VENTING DOES NOT WORKThe usual advice is wrongA review of 154 studies found hitting a bag or going for a run does nothing.
-
PRIVATENothing is saved or sentFree, no account, no sign-up. Your result stays in your browser.
A 15-question self-check
Take the anger test
Fifteen statements about how your anger behaves — including the anger you swallow rather than show. About two minutes.
Your result
What the ranges mean
- 0–15 Anger well within the ordinary range
- 16–30 Some anger management difficulty
- 31–45 Significant anger pattern
- 46–60 Anger significantly affecting your life
Fifteen statements scored 0 to 4 give a total of 0–60. The questions cover four things rather than one: how often anger fires, how big it is next to whatever caused it, how long it takes to clear, and what it has cost you in relationships, work and health. Two of them ask about anger you keep in rather than let out, because that version does damage too and most anger tests miss it.
Across 154 studies, activities that lower arousal reduced anger. Activities that raise it scored −0.02 — nothing.
The short answer
What is an anger problem?
Anger that is out of proportion to what caused it, happens more often than circumstances warrant, takes an unusually long time to subside, or produces behaviour that damages your relationships, your work or your health. None of those is a diagnosis, and anger has no diagnosis of its own — it is a normal emotion, and no manual lists “anger disorder”. What exists instead are conditions in which anger is a prominent feature, and the more ordinary situation in which anger is simply costing someone more than they want to pay. This test is about the second.
The four parts are worth separating because people usually have a problem with one of them rather than all four. Plenty of people get angry often and recover in a minute. Plenty get angry rarely and then cannot put it down for three days. The first group and the second need completely different help, and a single number cannot tell them apart — which is why the result talks about which part, not just how much.
The question is not whether you get angry. It is whether the anger is proportionate, and whether you can stop it.
Kjaervik and Bushman, 2024 is the source for what this page says about what helps: a review of 154 studies, 184 samples and 10,189 participants, finding that arousal-decreasing activities reduce anger and aggression while arousal-increasing ones do not.
View sourceThe four parts
What the fifteen questions ask about
Four separate things, and most people have trouble with one or two rather than all of them.
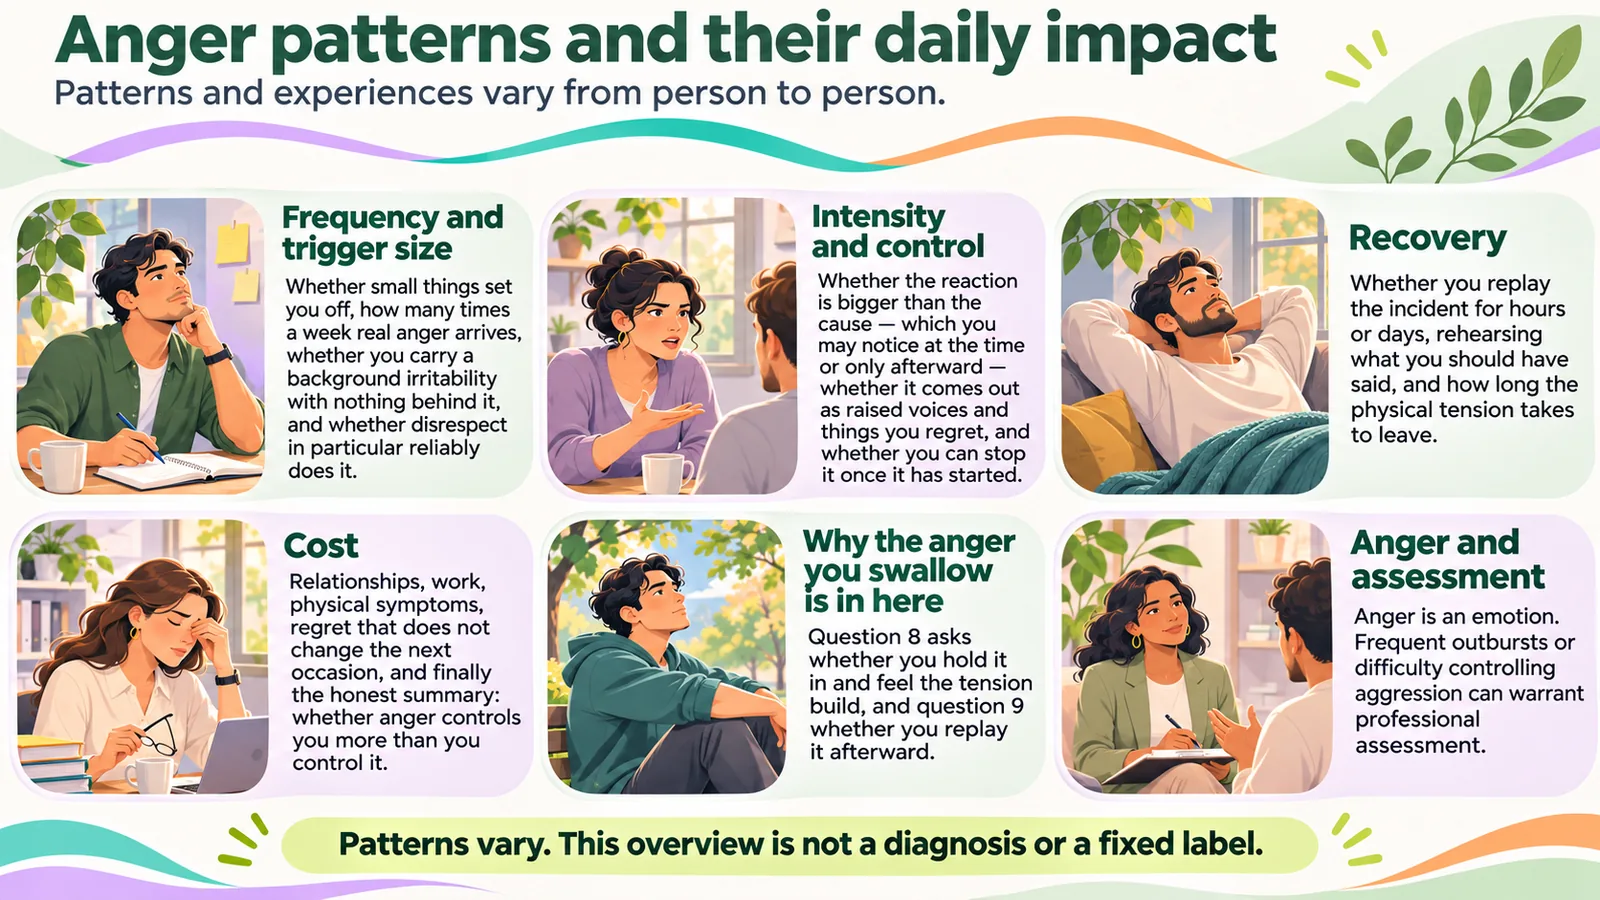
Frequency and trigger size (questions 1–5)
Whether small things set you off, how many times a week real anger arrives, whether you carry a background irritability with nothing behind it, and whether disrespect in particular reliably does it. Question 5 earns its place: for a lot of people the whole pattern runs on feeling dismissed.
Intensity and control (questions 3, 6, 7)
Whether the reaction is bigger than the cause — which you may notice at the time or only afterwards — whether it comes out as raised voices and things you regret, and whether you can stop it once it has started. Question 7 is the one that most separates a bad habit from a real problem.
Recovery (questions 9, 10)
Whether you replay the incident for hours or days, rehearsing what you should have said, and how long the physical tension takes to leave. Two people can be equally angry and differ entirely here, and the slow recoverer pays far more for the same number of incidents.
Cost (questions 11–15)
Relationships, work, physical symptoms, regret that does not change the next occasion, and finally the honest summary: whether anger controls you more than you control it. The last question is the one people answer most accurately, because by then they have stopped defending.
Why the anger you swallow is in here
Question 8 asks whether you hold it in and feel the tension build, and question 9 whether you replay it afterwards. Those two describe a pattern that never raises its voice and still costs a marriage. Most anger tests only measure the loud version.
Why there is no diagnosis to find
Anger is an emotion, not a condition, and there is no “anger disorder” to screen for. Where anger is severe and explosive it may be part of something with a name, but the far commoner case is anger that is simply expensive, and that does not need a label to be worth changing.
Anger, depression and trauma
Three things that produce a short fuse, for different reasons.
| Pattern | What it looks like | What it means |
|---|---|---|
| An anger pattern | Anger out of proportion, slow to clear, costing you things. | Worth changing. Responds well to CBT-based programmes. |
| Depression | Constant irritability, flat mood, nothing enjoyable, poor sleep. | Treatable, and a different conversation. See a doctor. |
| Trauma | Anger that arrived after something happened, with a hair trigger. | The trauma is the problem; the anger is the symptom. |
| How do I tell an anger problem from depression? | By what else is in the picture. Irritability is one of depression’s commonest features, and in men it is often the most visible one — so a short fuse that arrived alongside flat mood, lost interest, bad sleep and no appetite is usually depression wearing anger’s clothes. Treating the mood generally settles the fuse. Anger as its own pattern tends to come with ordinary mood in between the episodes. | |
Reading your result
What should you take from the number?
Three things more useful than the total.
- 01 Which of the four parts is yours
Frequency, size, recovery or cost
A person who flares ten times a day and recovers in a minute has a different problem from one who flares monthly and cannot put it down. Knowing which you are is more useful than the total and it points at different help.
- 02 Whether it goes out or in
Opposite problems, opposite fixes
Expressed anger needs the gap before the reaction. Swallowed anger needs the opposite — saying the thing at the time, in a smaller version, before it compounds into resentment. Questions 6 and 8 separate these.
- 03 What the people around you would say
The measure that counts
If the people you live with have become careful of you — watchful, placating, quieter when you come in — that is the finding that matters most and it is not on this page, it is in your house.
It cannot diagnose anything, because anger has no diagnosis. It cannot tell whether your anger is proportionate, since it only has your view of the situations and anger reliably distorts that view at the time. It cannot distinguish an anger pattern from depression or trauma, which both produce the same short fuse. And it measures no risk to anyone else — if your anger frightens the people around you, that is true whatever the number says.
Things people ask early
The questions that come up first
Three worth answering before the detail.
Does venting help?
No. A 2024 review of 154 studies found that activities raising arousal — hitting a pillow, punching a bag, going for a hard run — had essentially no effect on anger.
Is being angry a mental illness?
No. Anger is a normal emotion and has no diagnosis of its own. It can be a prominent feature of other conditions, which is a different thing.
Can anger actually be changed?
Yes, and unusually reliably. The NHS describes anger management as one-to-one counselling plus group work, mostly built on CBT, from a single day to a few months.
What works
What actually reduces anger
This is one of the few places where the evidence contradicts the popular advice outright.
- 01 / START HERE
Turn the arousal down, not up
Kjaervik and Bushman’s 2024 review pooled 154 studies and 10,189 participants. Activities that lower arousal — slow breathing, mindfulness, meditation, yoga — reduced anger and aggression with an effect size of −0.63, and held up across ages, genders, cultures, offenders and non-offenders, however they were delivered. Activities that raise arousal came out at −0.02. That is nothing.
- 02 / THE GAP BEFORE THE REACTION
Count, breathe, and leave the room
The NHS advice is unglamorous and it is the same mechanism: notice the build early, give yourself time before reacting, count to ten, use a calming breathing exercise. What makes it work is not the counting. It is that arousal falls while you are doing it, which is exactly what the meta-analysis found.
- 03 / GET THE PROGRAMME
And treat what is underneath
A GP can refer you to an anger management programme — one-to-one plus group, mostly CBT. If low mood, lost interest or poor sleep came with the anger, treat that first; the fuse usually shortens because of the depression rather than the other way round. And the NHS is specific that alcohol, cigarettes, gambling and drugs all make anger worse, however much they help in the hour.
Background: NHS, Anger. This page is educational and is not medical advice.
What to do next
What should you do with your result?
Three things, whatever the number said.
- 142
Name which of the four parts is yours
Frequency, size, recovery, or cost. One sentence. It is the difference between useful help and generic advice.
- 02
Try the boring thing for two weeks
Slow breathing when you feel it building. It is the intervention with the evidence behind it, and it costs nothing to test.
- 03
Ask one person who lives with you
Not whether you have an anger problem — whether they ever change what they do to avoid setting you off. That answer is the real score.
Two things that need more than a questionnaire. If shouting, threats, breaking things or physical force are part of how your anger comes out, that is frightening to live with whatever you intended, and the NHS lists acting in an abusive or violent way alongside not coping as a reason to see a GP. In the US the National Domestic Violence Hotline is free and confidential on 1-800-799-7233, or text START to 88788 — and they take calls from people worried about their own behaviour, not only from people on the receiving end. And if your anger turns inward instead, the NHS lists self-harm among the things it can lead to: if you have been hurting yourself or thinking about it, call or text 988 in the US for the Suicide and Crisis Lifeline, or 116 123 for Samaritans in the UK. Elsewhere, find a line at findahelpline.com. Asking for help with anger is not an admission that you are a bad person. It is the thing that changes the next argument.
Good questions to ask
Anger management test — FAQs
What people actually ask about anger.
No, and this is the clearest finding on the page. Kjaervik and Bushman’s 2024 meta-analysis pooled 154 studies, 184 samples and 10,189 participants, and found that arousal-increasing activities — hitting a bag, punching a pillow, going for a hard run — produced an effect on anger of −0.02, which is indistinguishable from nothing. Arousal-decreasing activities came out at −0.63. In the authors’ own words, the findings do not support the idea that venting anger or going for a run are effective anger management activities. If anything, rehearsing the anger keeps it alive.
Not as such. Anger is a normal emotion and no diagnostic manual lists an “anger disorder”. What exists are conditions in which anger is a prominent feature — intermittent explosive disorder is the one most often meant, and depression, PTSD and several others routinely show up as a short fuse. The commonest situation by far, though, is anger that is not part of any condition and is simply costing someone more than they want to pay. That does not need a diagnosis to be worth changing.
There is no number, and anyone offering one is guessing. Anger is appropriate when something unfair has happened and proportionate to how unfair it was. The useful test is not frequency but fit: does the size of the reaction match the size of the cause, does it pass when the situation resolves, and does it leave damage behind. Someone who is angry daily in genuinely infuriating circumstances is responding correctly. Someone who is angry monthly and loses a friendship each time is not.
Because recovery is a separate trait from intensity, and this test measures them separately for that reason. Two people can reach the same peak and take wildly different times to come down. Rumination is the usual mechanism — replaying the incident, rehearsing the reply you did not give — and it keeps physiological arousal up, which is why the anger persists. The arousal-decreasing activities that work on anger in the moment are the same ones that shorten this.
It might well be, and this is the single most missed thing on the subject. Irritability is a core feature of depression, and in men it is frequently the most visible symptom — more visible than sadness. The distinguishing question is what sits between the episodes: anger as its own pattern leaves ordinary mood in between, while depression leaves flat mood, lost interest, poor sleep and no appetite. Our Clinical Depression Test is the place to check.
The question asks about physical symptoms — headaches, jaw tension, muscle tightness — and the NHS lists a faster heartbeat, tense muscles, clenched fists, chest tightness and feeling hot among anger’s physical effects. Those are real and immediate. Claims about anger causing specific long-term disease are commonly made and we are not making them here, because we did not find a source for them that we could check.
The NHS describes it as a mix of one-to-one counselling and group work, running anywhere from a single day or weekend to a couple of months, with most programmes built on cognitive behavioural therapy. A GP can refer you. If you go privately, check the therapist is registered with a professional body.
Yes. The test is free, needs no account or sign-up, and your result appears only in your browser. Nothing is sent to us.
Because they are safe, in the narrow sense that the relationship survives it. Most people regulate perfectly well at work all day and lose it at home, which is less a fact about the family than about where the restraint ran out. It is worth saying plainly that this is the most expensive place to spend your anger, since the cost accumulates in the relationships you least want to damage.
Editorial transparency
Sources and review information
The fifteen statements cover frequency, intensity, recovery and cost, and were written for this site. They are not a clinical instrument and no score here is diagnostic — nor could it be, since anger has no diagnosis. What the page states about what helps, and about anger’s symptoms and treatment, comes from the two sources listed. Written and reviewed by the PsyMed Editorial Team. We are writers and researchers, not clinicians, and this page is educational rather than diagnostic. Read how we build our tests and who we are.
Research and editorial references
- Kjaervik SL & Bushman BJ (2024). A meta-analytic review of anger management activities that increase or decrease arousal: What fuels or douses rage? Clinical Psychology Review 109:102414 — the source for everything this page says about what works: 154 studies, 184 independent samples, 10,189 participants; arousal-decreasing activities at g = −0.63 (95% CI −0.82 to −0.43) and arousal-increasing activities at g = −0.02 (−0.13 to 0.09); effects stable across gender, race, age and culture, and in offenders as well as non-offenders. doi.org/10.1016/j.cpr.2024.102414
- NHS, Anger — the source for the physical, mental and behavioural symptoms, the self-help list, the four things not to do, the point that some people direct anger outward and others hide it and take it out on themselves, when to see a GP (including acting in an abusive or violent way), and what an anger management programme involves. nhs.uk/mental-health/feelings-symptoms-behaviours/feelings-and-symptoms/anger
- This page publishes no prevalence figure for anger problems, no diagnostic criteria for intermittent explosive disorder, and no claim that anger causes any specific long-term illness. Those claims are common on this subject and we did not find sources for them that we had checked, so they are left out.
- The strongest claim here runs against the usual advice, so it is worth being exact about it: venting was measured and it did not work. That is one meta-analysis, not a law of nature, but it is the best evidence available and it is unambiguous.
A questionnaire, not a verdict
Anger is the emotion that registers unfairness. The problem is only ever its size, its length and where it lands.
If your result pointed that way, the useful next steps are naming which of the four parts is yours, trying the slow-breathing thing for a fortnight, and asking one person who lives with you whether they ever change what they do to avoid setting you off.
Take the test