
Self-check · Anxiety & OCD
OCD Test: the thought is not the disorder, the loop is
Unwanted thoughts about harm, contamination or blasphemy occur in people with no disorder at all. These 20 questions ask about what follows one — the anxiety, the ritual, the brief relief — and how much of your day it takes.

Not a diagnosis and not the Y-BOCS. Our questions are our own, so these five ranges are descriptive rather than validated thresholds.
-
INTRUSIVE THOUGHTS ARE NORMALThe thought is not the disorderWhat makes it OCD is the cycle that follows it, not the thought itself.
-
NOT THE Y-BOCSThese ranges are descriptiveOur questions are our own, and no cut-off here is a validated threshold.
-
PRIVATENothing is saved or sentFree, no account, no sign-up. Your result stays in your browser.
A 20-question self-check
Take the OCD self-check
Twenty statements about intrusive thoughts and the things you do in response. About three minutes.
Your result
What the ranges mean
- 0–15 Little sign of the cycle
- 16–31 The cycle is present and mild
- 32–47 Taking real time and effort
- 48–63 Substantially shaping your days
- 64–80 Dominating your daily life
Twenty statements scored 0 to 4 give a total of 0–80. Ten ask about the shape of the cycle — how much time it takes, how much it interferes, how distressing it is, how hard you resist, how much say you have — and ten ask what the thoughts and behaviours actually are.
Across 36 trials and 2,020 patients. The size depends heavily on what it is compared with.
The short answer
What is OCD?
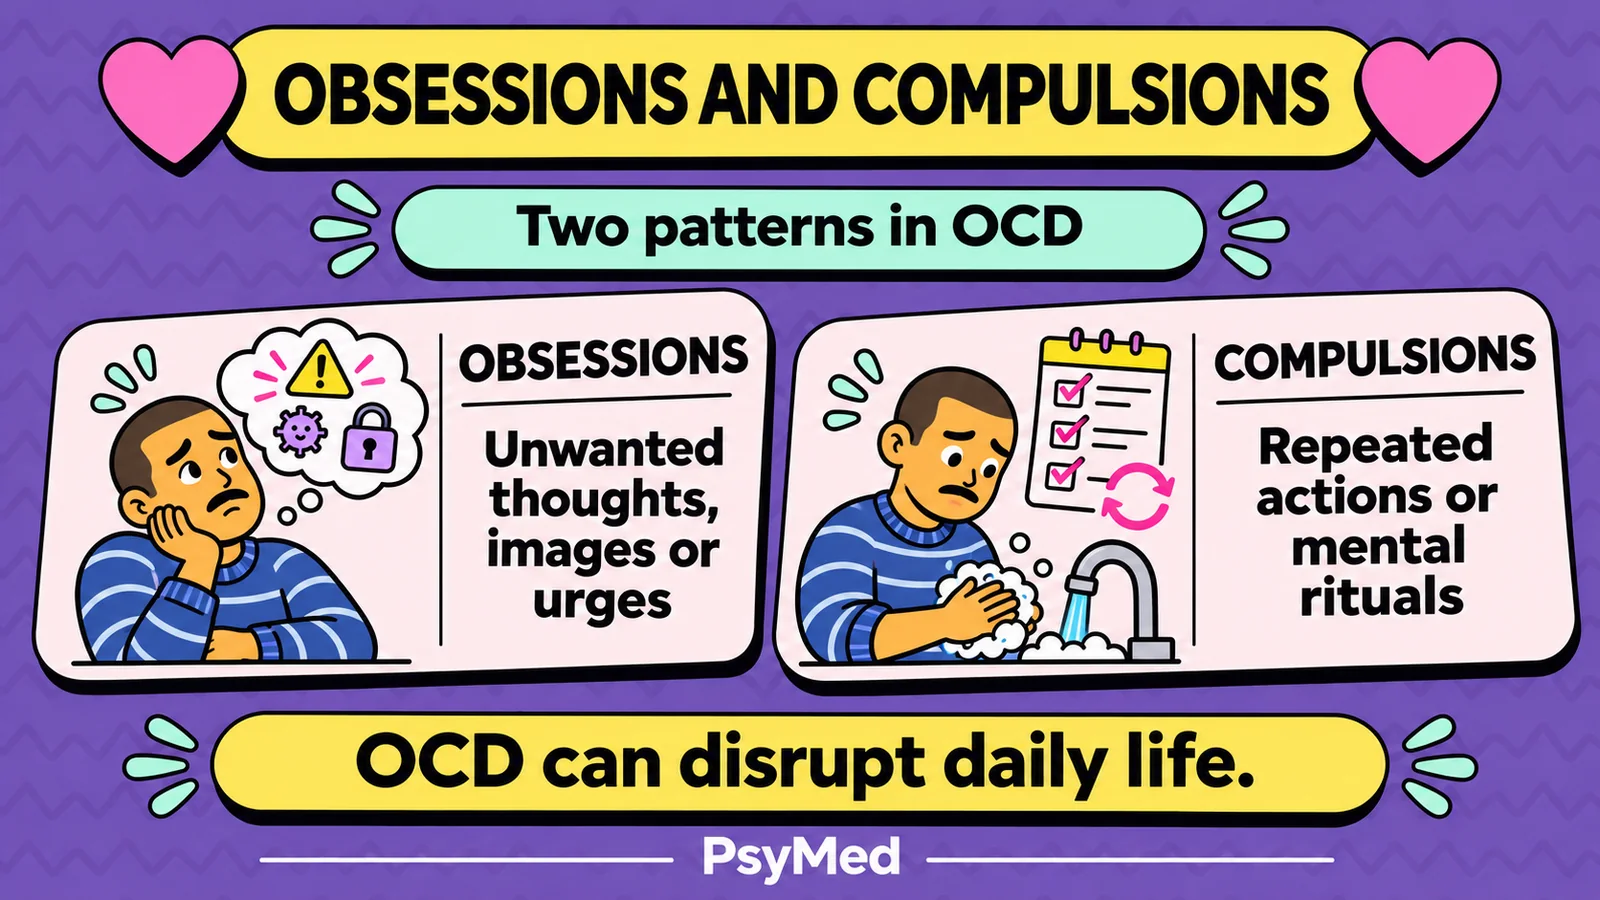
A condition in which unwanted intrusive thoughts, images or urges (obsessions) drive repetitive behaviours or mental acts performed to reduce the distress they cause (compulsions), in a loop that consumes time and interferes with life. NIMH estimates that 1.2 per cent of US adults had OCD in the past year and 2.3 per cent at some point in their lives, and says symptoms usually begin between late childhood and young adulthood. Of those with OCD in a given year, NIMH reports 50.6 per cent had serious impairment.
The ten dimensions are worth separating because severity is not one thing. Someone can spend two hours a day on rituals and resist them hard, or twenty minutes and feel entirely unable to stop. Those are different problems and they come apart.
The question is not whether you have had the thought. It is how much of your day the response to it takes.
Reid and colleagues, 2021 is the source for what this page says about treatment: a meta-analysis of 36 randomised trials and 2,020 patients finding a large pooled effect for CBT with exposure and response prevention against control conditions (g = 0.74), with the size depending substantially on the comparator.
View sourceThe ten dimensions
What the twenty questions ask about
Ten about the shape of the cycle, ten about its content.

The obsession side (questions 1–5)
How much of the day intrusive thoughts take up, how much they interfere with work and responsibilities, how much distress they cause, how hard you try to push them away, and how much say you have over them once they start.
The compulsion side (questions 11–15)
The same five questions about the things you do in response — washing, checking, counting, re-reading, reassurance-seeking, mental reviewing: time, interference, distress at stopping, effort to resist, and how much say you have.
What the thoughts are about (questions 6–10)
Contamination, unwanted thoughts of harm, the sense that things are not right, thoughts of a sexual, violent or blasphemous kind that run against your values, and unresolvable doubt about whether you did something.
What the behaviours are (questions 16–20)
Washing and cleaning, checking, arranging and repeating until it feels right, reassurance-seeking and mental rituals, and finally how much the need to perform them has shaped your life over the past week.
Why the content questions matter less than they look
Questions 7 and 9 ask about thoughts of harm and about sexual, violent or religious intrusions. Those are the thoughts people are most frightened to admit to, and they are also among the commonest in the general population. A high answer there is not evidence of danger or of character. The ten cycle questions are the ones that describe a disorder.
Why these five ranges are not a severity scale
The five labels here are descriptive and they are not clinical thresholds. The well-known severity bands for OCD belong to the Y-BOCS, a ten-item clinician-administered scale, and were validated for it. This is a twenty-item self-report with ten additional content questions, so those thresholds do not transfer to it and this page does not pretend otherwise.
OCD, OCPD and general anxiety
Three things confused with each other constantly.
| Pattern | What it looks like | What it means |
|---|---|---|
| OCD | Unwanted intrusive thoughts and rituals done to relieve them. Ego-dystonic. | A condition, and among the more treatable ones. |
| OCPD | Orderliness, control and perfectionism experienced as how one ought to be. | A personality style, not the same thing. Different route in. |
| Generalised anxiety | Worry across many real-life areas, without rituals attached. | A different condition. No compulsion loop. |
| How do I tell OCD from being a tidy or careful person? | By whether it is wanted. The usual word is ego-dystonic: OCD thoughts feel alien and unwelcome, and the rituals are done to make the distress stop rather than because you want to do them. Someone with an orderly temperament experiences their standards as their own preference. The other test is cost: liking a tidy flat takes no time out of your week, and a checking ritual does. | |
Reading your result
What should you take from the number?
Three things more useful than the total.
- 01 Hours, not score
Questions 1 and 11
How much of your day the thoughts and the rituals take is the thing a clinician will ask about first, and it is the single most informative answer on the page. Hours per day is a sentence you can take to an appointment; a score out of eighty is not. more useful than the total because it is the number they actually use.
- 02 Resistance and control are separate
Trying hard is not the same as succeeding
Questions 4, 5, 14 and 15 split effort from outcome on purpose. Fighting the compulsion constantly and losing is a different picture from not fighting it, and the two need different conversations.
- 03 What it has removed from your life
The measure that counts
Question 20 asks what the rituals have cost you over the past week in choices and freedom. If the honest answer is a great deal, that is the finding that matters most whatever the total came to.
It cannot diagnose OCD, and it cannot produce a Y-BOCS score or anything comparable to one. It cannot tell OCD apart from health anxiety, generalised anxiety or an eating disorder with ritualised features, all of which can produce similar answers. And it cannot tell you whether an intrusive thought means anything — it does not, which is the point of the whole page.
Things people ask early
The questions that come up first
Three worth answering before the detail.
Does having a violent or sexual intrusive thought mean something is wrong with me?
No. Unwanted intrusive thoughts of that kind occur in people with no disorder at all, and in OCD the distress they cause is precisely because they run against your values. The thought is not a wish and it is not a plan.
Is OCD common?
NIMH puts past-year prevalence among US adults at 1.2 per cent and lifetime at 2.3 per cent. The IOCDF phrases the same territory as about 1 in 40 adults currently having OCD, over three million US adults.
Can it be treated?
Yes. The IOCDF describes exposure and response prevention as the proven, most effective first-line therapy for OCD, and medication is used alongside it.
What works
What actually reduces OCD
One named therapy, and an honest account of how strong the evidence for it is.
- 01 / START HERE
Ask for ERP by name
Exposure and response prevention is the specific therapy for OCD — the IOCDF calls it the proven, most effective, first-line therapy for it — and it is not the same as general counselling or generic CBT. Asking for it by name matters, because the mechanism is particular: you approach the trigger and do not perform the ritual, until the anxiety falls on its own. Reid and colleagues’ meta-analysis of 36 trials found a large pooled effect against control conditions, g = 0.74. Be aware the figure moves with the comparator — see the note below — but ERP remains the treatment to ask for. raise arousal came out at −0.02. That is nothing.
- 02 / BE HONEST ABOUT THE EVIDENCE
Large against placebo, less against other therapy
Reid and colleagues found g = 1.13 against psychological placebo, but g = −0.05 against other active psychological therapies and g = 0.32 against adequate doses of medication, with the confidence interval touching zero. Trials where researcher allegiance was suspected gave g = 0.95; the eight without it gave g = 0.02, and only eight of thirty-six were judged at low risk of bias. That does not mean ERP does not work. It means the honest claim is that it is the best-evidenced OCD-specific therapy, not that it is proven superior to everything else.
- 03 / MEDICATION AND WHO TO CALL
SSRIs, and the IOCDF directory
SSRIs are the medication class used for OCD and are often combined with ERP; which one is a decision for a prescriber, and this page deliberately names none. To find someone who actually does ERP, the International OCD Foundation keeps a specialist directory at iocdf.org/find-help. Their office number is 617-973-5801 — useful for reaching the Foundation, but it is not a crisis line.
Background: IOCDF, About OCD. This page is educational and is not medical advice.
What to do next
What should you do with your result?
Three things, whatever the number said.
- 01
Work out the hours
How long the thoughts and the rituals take on a normal day. One number. It is the thing a clinician asks first and the thing a score cannot replace.
- 02
Ask for ERP, by name
Not counselling, not generic CBT. Exposure and response prevention. The IOCDF directory at iocdf.org/find-help lists people who do it.
- 03
Stop asking for reassurance
Reassurance-seeking is itself a compulsion — question 19 asks about it. It relieves the anxiety briefly and strengthens the loop, which is why ERP targets it directly.
Intrusive thoughts about harm are one of the commonest forms OCD takes and they are not intentions — but if you are having thoughts of ending your life, or the condition has reached the point where you cannot function, that needs attention today rather than at the next appointment. 988 in the US for the Suicide and Crisis Lifeline, by call or text, or 116 123 for Samaritans in the UK. Elsewhere, find a line at findahelpline.com. OCD is one of the most treatable conditions in this field, and severity at any level is a reason to get help rather than evidence that help will not work.
Good questions to ask
OCD test — FAQs
What people actually ask about OCD.
No. The Yale–Brown Obsessive Compulsive Scale is a copyrighted clinician-administered instrument and its electronic use requires a licence we do not hold, so the twenty questions here are our own. That also means the five ranges on this page are descriptive rather than validated thresholds, and a score here cannot be compared with a Y-BOCS score. A clinician can administer the real thing.
No. Unwanted intrusive thoughts of harm, including violent and sexual ones, occur in people with no disorder, and in OCD the distress exists precisely because the thought is contrary to your values. People with OCD are not more likely to act on them; the fear of acting is a symptom, not a warning.
NIMH estimates 1.2 per cent of US adults had OCD in the past year — 1.8 per cent of women and 0.5 per cent of men — and 2.3 per cent at some point in life. Of those with past-year OCD, 50.6 per cent had serious impairment, 34.8 per cent moderate and 14.6 per cent mild.
Exposure and response prevention means approaching what triggers the obsession while deliberately not performing the ritual, until the anxiety subsides on its own. The reason the name matters is that general counselling does not do this, and reassurance — which a well-meaning therapist may offer — is itself the compulsion. The IOCDF describes ERP as the proven, most effective, first-line therapy for OCD.
Better than placebo by a wide margin and less clearly than people are usually told. Reid and colleagues pooled 36 trials and 2,020 patients: g = 0.74 against all controls and 1.13 against psychological placebo, but −0.05 against other active psychological therapies and 0.32 against adequate doses of medication. Trials with suspected researcher allegiance showed g = 0.95 and those without showed 0.02. It is the best-evidenced OCD-specific therapy; it is not proven superior to every alternative. OCPD Test is worth a look if the pattern is perfectionism rather than rituals.
NIMH says symptoms can begin at any time but usually start between late childhood and young adulthood.
Yes, and it is one of the most commonly missed. Asking a partner whether you locked the door, or whether a thought makes you a bad person, produces the same brief relief as a physical ritual and strengthens the loop the same way. Question 19 asks about it for that reason, and ERP targets it directly.
Yes. The test is free, needs no account or sign-up, and your result appears only in your browser. Nothing is sent to us.
It can be. Compulsions are not always visible — mental reviewing, silently repeating phrases, neutralising a bad thought with a good one and checking internally how you feel all count, and question 19 asks about them. “Purely obsessional” OCD is usually OCD with mental compulsions rather than none.
Editorial transparency
Sources and review information
The twenty statements were written for this site after the previous version was found to reproduce the Y-BOCS too closely; they cover the same ground in our own words. They are not a clinical instrument and no score here is diagnostic, nor comparable to a Y-BOCS score. What this page states about prevalence, onset and treatment comes from the sources below and is attributed in the text. Written and reviewed by the PsyMed Editorial Team. We are writers and researchers, not clinicians, and this page is educational rather than diagnostic. Read how we build our tests and who we are.
Research and editorial references
- Reid JE, Laws KR, Drummond L, Vismara M, Grancini B, Mpavaenda D & Fineberg NA (2021). Cognitive behavioural therapy with exposure and response prevention in the treatment of obsessive-compulsive disorder: a systematic review and meta-analysis of randomised controlled trials. Comprehensive Psychiatry 106:152223 — 36 studies, 2,020 patients. g = 0.74 against all controls, 1.13 against psychological placebo, −0.05 against other active psychological therapy, 0.32 against adequate-dose pharmacotherapy; g = 0.95 in trials with suspected researcher allegiance against 0.02 without; 8 of 36 at low risk of bias. The source for every treatment-effect figure here. doi.org/10.1016/j.comppsych.2021.152223
- National Institute of Mental Health. Obsessive-Compulsive Disorder — statistics and topic page. — past-year prevalence among US adults 1.2 per cent (women 1.8, men 0.5), lifetime 2.3 per cent; of those with past-year OCD, 50.6 per cent serious impairment, 34.8 per cent moderate, 14.6 per cent mild; symptoms usually begin between late childhood and young adulthood. nimh.nih.gov/health/statistics/obsessive-compulsive-disorder-ocd
- The International OCD Foundation (iocdf.org) is the source for the description of ERP as the proven, most effective first-line therapy, for the phrasing of prevalence as about 1 in 40 adults, for the specialist directory at iocdf.org/find-help, and for the office number 617-973-5801. The previous version of this page described that number as a helpline; it is the Foundation’s office line and not a crisis service.
- Two things this page deliberately does not do. It names no specific SSRI, because we could not verify a current guideline source today — NICE returns 403 to automated requests and NIMH’s OCD page names no medication — so the choice is left to a prescriber. And it does not present its five ranges as severity thresholds: the familiar OCD severity bands belong to the Y-BOCS, were validated for that ten-item clinician-administered scale, and do not transfer to a twenty-item self-report with ten extra content questions.
A questionnaire, not a verdict
The thought is not the disorder. The loop that follows it is, and that loop is one of the most treatable things in this field.
If your result pointed that way, the useful next steps are working out the hours, asking for ERP by name, and stopping the reassurance-seeking that keeps the loop fed.
Take the test