



Free Social Anxiety Test — Social Anxiety Disorder Self-Assessment
Does fear of judgment stop you from living fully? This free Social Anxiety Test covers all DSM-5-TR criteria for SAD — 15 questions inspired by LSAS and SPIN.
Published Updated
A screening tool for self-reflection, not a diagnosis. How we build our tests
Most people feel nervous before a job interview, a first date, or a public presentation. That kind of situational anxiety is normal — it fades once the situation passes. But for millions of people, social anxiety goes far deeper. The fear of being judged, embarrassed, or humiliated is so strong and lasting that it shapes every choice: which events to skip, which friendships to give up, which chances to quietly let pass. The anxiety doesn’t fade with the situation. It grows with every avoidance.
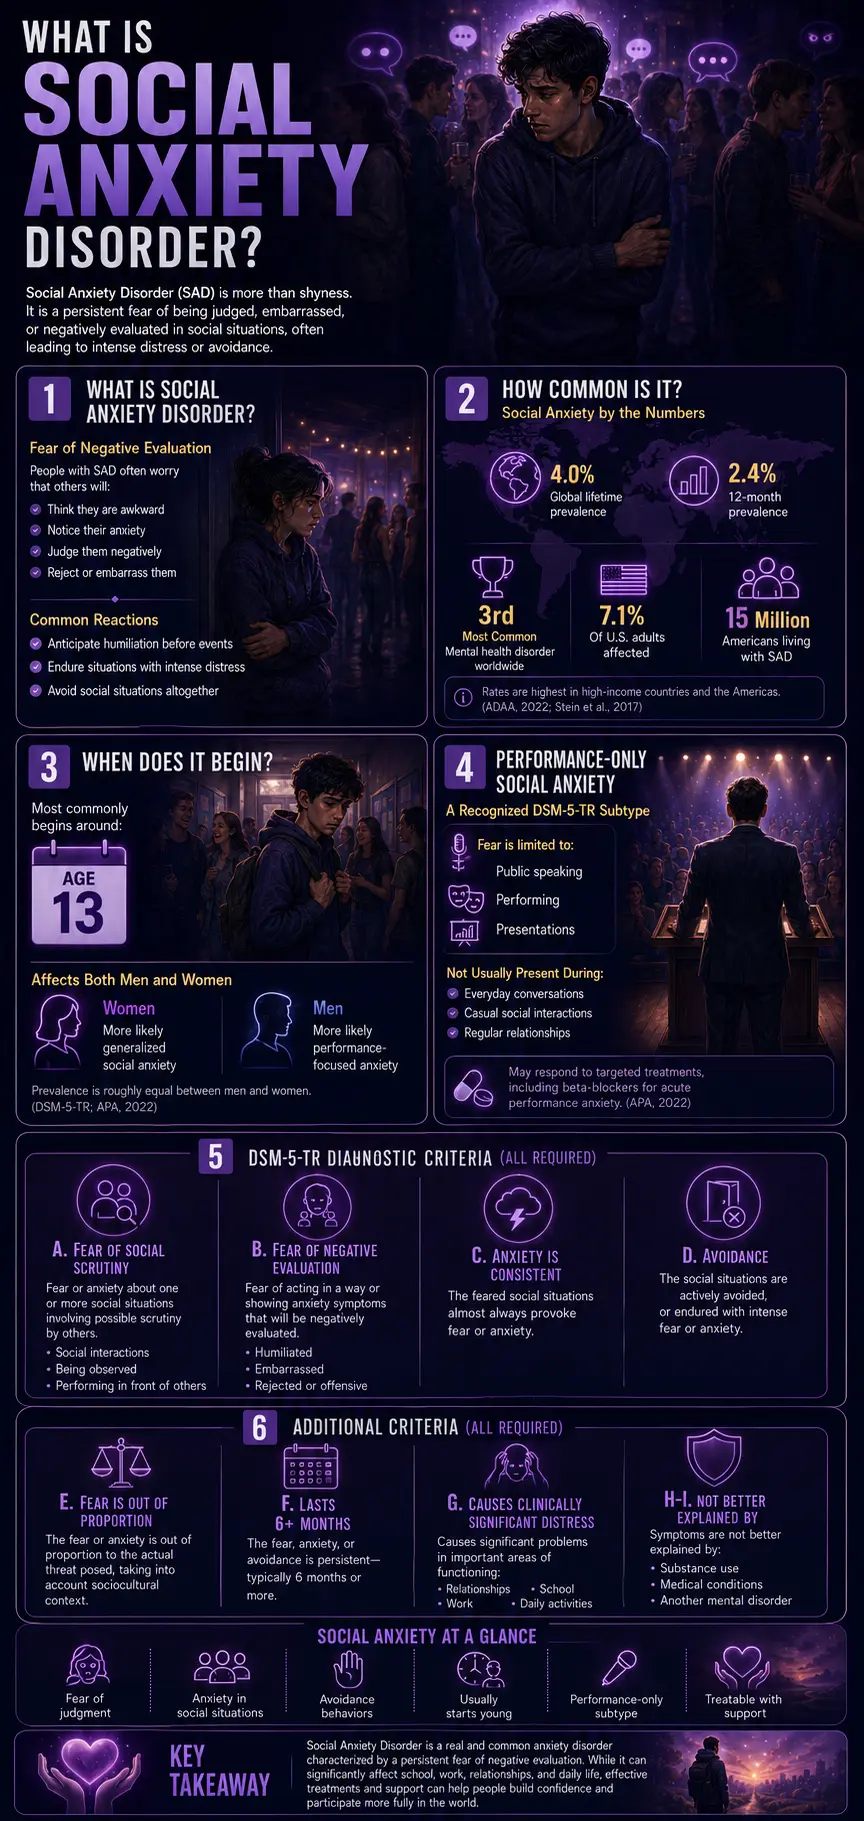
Social Anxiety Disorder is the third most common mental health disorder in the world, after depression and alcohol use disorder, affecting approximately 15 million US adults — around 7.1% of the population (ADAA, 2022). Yet the average person with social anxiety waits over ten years before seeking help. Many believe the fear is simply who they are, not a known condition that responds well to treatment (ADAA, 2022).
This free Social Anxiety Test covers all DSM-5-TR criteria for Social Anxiety Disorder (APA, 2022). It is inspired by the two most widely used screening tools for Social Anxiety Disorder (SAD): the Liebowitz Social Anxiety Scale (LSAS; Liebowitz, 1987) and the Social Phobia Inventory (SPIN; Connor et al., 2000). 15 questions. Based on the past 6 months. Instant, private results.
What Is Social Anxiety Disorder?
Social Anxiety Disorder (SAD) — DSM-5-TR code 300.23 (F40.10), once also called “social phobia” in earlier DSM editions — is an anxiety disorder. It involves strong, lasting fear of social or performance situations where others might watch or judge you. The fear is about being judged badly: seen as incompetent, awkward, embarrassing, or offensive. People with SAD anticipate humiliation before social situations, endure them with intense distress, or avoid them altogether (APA, 2022).
SAD is the third most common mental health disorder worldwide, after depression and alcohol use disorder (ADAA, 2022). Global lifetime prevalence is 4.0%, and 12-month prevalence is 2.4%, based on the World Mental Health Survey Initiative covering 28 countries and 142,405 respondents (Stein et al., 2017, Psychological Medicine).
Rates are higher in high-income countries and the Americas. In the United States, approximately 7.1% of adults — around 15 million people — are affected (ADAA, 2022). Onset is typically early: the disorder most commonly begins around age 13. Rates are roughly equal between men and women. Women more often have broad social anxiety, while men more often fear performing in particular (DSM-5-TR; APA, 2022).
The DSM-5-TR recognizes a “performance-only” specifier for cases where the fear is only about speaking or performing in public, not everyday social contact. This subtype is a bit different and may respond to specific treatments, including beta-blockers for stage fright in the moment (APA, 2022).
The full DSM-5-TR diagnostic criteria for SAD (all of the following required; APA, 2022):
- Criterion A: Strong fear or anxiety about one or more social situations where others might watch or judge the person: talking with people, being watched, or performing in front of others.
- Criterion B: The person fears they will act in a way, or show anxiety, that others will judge badly. They fear being humiliated, embarrassed, rejected, or seen as offensive.
- Criterion C: The feared social situations almost always provoke fear or anxiety.
- Criterion D: The social situations are actively avoided or endured with intense fear or anxiety.
- Criterion E: The fear or anxiety is out of proportion to the actual threat posed, taking into account sociocultural context.
- Criterion F: The fear, anxiety, or avoidance is persistent — typically 6 months or more.
- Criterion G: Causes clinically significant distress or impairment in social, occupational, or other important areas of functioning.
- Criteria H–I: Not better explained by substances, a medical condition, or another mental disorder.
Signs You Might Have Social Anxiety Disorder
Social anxiety is often missed. People who have it put it down to shyness or introversion. Doctors may not ask enough to tell normal social unease from the disorder. These are the clearest signs that SAD may be present.
The anticipatory anxiety is often worse than the situation itself. Days or weeks before a social event, the dread arrives. Mental rehearsal of worst-case scenarios: saying the wrong thing, going blank, visibly shaking, being judged. The anxiety before is intense enough that many people cancel plans simply to relieve it — which provides immediate relief and reinforces the avoidance cycle. This anticipatory pattern, extending well beyond the situation itself, is one of the most clinically specific features of SAD. Normal situational nervousness doesn’t begin a week in advance.
In social situations, your attention turns sharply inward. Instead of focusing on the conversation, much of your mind is busy watching yourself. How am I coming across? Do I look nervous? Is my voice shaking? Am I saying the right things? This inward focus is both a symptom and part of what keeps the anxiety going. It uses up the attention you need to actually take part, which makes the anxiety worse and the conversation more awkward.
Physical symptoms appear reliably in feared social situations. Blushing, sweating, trembling, racing heart, nausea, voice shaking, dry mouth. These symptoms are upsetting in themselves. For people with Social Anxiety Disorder (SAD), they are worse because of the fear that others will notice them. So there is a second fear, of looking anxious, on top of the main fear of being judged. The body’s symptoms become part of what is feared.
You replay social situations afterward — and the replay is harsh. After a social event, the post-event processing begins: a detailed review of every perceived mistake, embarrassing moment, or wrong thing said. The review is systematically distorted — negatives are amplified and made central, positives are dismissed or minimized as flukes. This post-event processing maintains SAD by reinforcing negative beliefs about social performance and making the next similar situation feel even more threatening. It is a cognitive maintenance mechanism that keeps the disorder active even when no social situation is currently happening.
The fear extends across multiple social situation types. SAD is not just fear of public speaking, though that is common. It covers the five areas of the LSAS:
- speaking or performing in public
- eating or drinking in front of others
- standing up for yourself (disagreeing, returning items, asking questions)
- working or writing while being watched
- talking with strangers or people you don’t know well
The generalized subtype of SAD involves fear in most or all of these areas. The performance-only specifier covers only public speaking and performing. If your fear shows up in most social settings, that breadth is an important sign.
You avoid situations or activities specifically because of social anxiety. Job opportunities, social events, romantic possibilities, classes, or professional situations that would require being in a feared situation. The avoidance may be obvious (not going to parties) or subtle (attending but staying on the periphery, not contributing to conversations, leaving early). DSM-5-TR Criterion D — active avoidance or endurance with intense distress — is met either way. The avoidance is relief-seeking behavior that maintains the disorder by preventing the disconfirming experience of tolerating anxiety until it naturally decreases.
The fear is out of proportion to the actual threat — and you know it. DSM-5-TR Criterion E requires that the fear be out of proportion to the real danger. Many people with SAD know their fear is too much: “I know rationally that speaking in this meeting is not dangerous, but I feel as if it is.” Knowing this doesn’t reduce the fear. It adds self-criticism (why can’t I just be normal?), which can make the distress worse.
The pattern has been present for at least six months and is affecting your life. Criterion F (lasting 6 months) and Criterion G (affecting daily life) together set SAD apart from a short anxious spell. If the social fear has been there steadily for more than six months and is affecting your work, relationships, or daily life, that matters, however long ago it started.

Social Anxiety vs Shyness vs Agoraphobia vs AVPD
| Feature | Social Anxiety Disorder (SAD) | Shyness (Trait) | Agoraphobia | Avoidant PD (AVPD) |
|---|---|---|---|---|
| Core fear | Negative evaluation — being judged as embarrassing, incompetent, or offensive | Social discomfort — not a fear of evaluation per se, but inhibition in unfamiliar contexts | Being in situations where escape is difficult or help is unavailable — not about judgment | Inadequacy and negative evaluation — same as SAD but more pervasive and identity-level |
| Functional impairment | Required for diagnosis — clinically significant distress or impairment (Criterion G) | Not required — shy people typically function well without clinically significant impairment | Required — avoidance restricts mobility and daily independence | Required — pervasive avoidance affects work and relationships across domains |
| Does anxiety ease with familiarity? | Often yes — people with SAD may feel relatively comfortable with close friends; the fear is typically context-specific | Yes — shyness typically reduces substantially as situations become familiar | Not primarily about familiarity — the fear is about the situation’s escape properties, not the people in it | Partially — AVPD involves pervasive interpersonal inadequacy that doesn’t ease fully even in long-standing relationships |
| Companion effect | Having a trusted companion may ease anxiety in social situations, but it is not a required feature | Often helps — social support reduces inhibition | A trusted companion specifically enables entry into avoided situations — this is a diagnostic feature of agoraphobia | Companions help less than in SAD — the feelings of inadequacy are more pervasive and internal |
| DSM-5-TR classification | Anxiety disorder — 300.23 (F40.10) | Not a disorder — normal personality trait | Anxiety disorder — 300.22 (F40.00) | Cluster C personality disorder — 301.82 (F60.6) |
| Duration criterion | 6+ months (Criterion F) | No criterion — trait, not disorder | 6+ months (DSM-5-TR) | Since early adulthood — pervasive, lifelong pattern |
| PsyMed test | This test | N/A | Agoraphobia Test | Avoidant PD Test |
The difference between SAD and AVPD needs special attention. Both share the same core fear, of being judged badly, and lead to similar avoidance. That is why many clinicians and patients can’t tell them apart on the surface. The key differences: SAD is an anxiety disorder. It comes and goes, is tied to certain situations, and usually responds to CBT in 12–16 sessions. AVPD is a personality disorder. It is everywhere, part of a person’s identity, and needs longer schema-focused or psychodynamic therapy.
SAD and AVPD often occur together. Estimates of overlap range from 25–89%, depending on the criteria (DSM-5-TR notes they may be different forms of the same underlying vulnerability). Does the avoidance feel less like situational anxiety and more like a core part of who you are, present in almost every relationship and setting since early adulthood? If so, the Avoidant Personality Disorder Test is worth completing alongside this one.
What Causes Social Anxiety Disorder?
SAD etiology is well characterized, involving the interaction among biological vulnerability, cognitive patterns, and developmental experience.
Genetic and biological factors. SAD has significant heritability — estimated at 30–40% in twin studies. First-degree relatives of people with SAD have higher rates of the disorder. Neurobiologically, the amygdala — the brain’s threat-detection center — shows heightened reactivity to social threat cues in people with SAD, including faces, social scenarios, and negative evaluation feedback. The serotonergic and dopaminergic systems are implicated, which aligns with the pharmacological response to SSRIs (first-line pharmacotherapy for SAD).
Cognitive maintaining factors. The most influential thinking model of SAD comes from David M. Clark and Adrian Wells (1995, Behaviour Research and Therapy), later refined by Clark (1999, 2001). The Clark-Wells model names three things that keep SAD going:
- Focusing on yourself, which leaves less attention for the people around you.
- Using “safety behaviors”: small actions meant to prevent a feared outcome, like gripping a cup so your hand doesn’t visibly shake, or avoiding eye contact. These keep anxiety going, because you never learn the feared outcome wouldn’t have happened anyway.
- Dreading events beforehand and replaying them afterward, which colors your memory and your expectations of the next time.
Developmental and behavioral factors. Behavioral inhibition in childhood — a temperamental tendency to withdraw from novel or unfamiliar stimuli — is one of the strongest developmental predictors of SAD. Specific learning experiences (public humiliation, being the target of bullying, embarrassing incidents in front of groups) can precipitate or intensify SAD. Parenting styles involving criticism, overprotection, or modeling of social anxiety also contribute.
Comorbidities. SAD has very high comorbidity rates. Major depressive disorder is the most common comorbidity — the social isolation and functional impairment of SAD predictably produce depression over time. Other anxiety disorders commonly co-occur, as do substance use disorders (alcohol is frequently used as a social anxiety management strategy). Avoidant Personality Disorder is the most common personality disorder comorbidity.

About This Test — LSAS and SPIN Framework
This Social Anxiety Test is inspired by the two most widely used clinical screening instruments for SAD:
The Liebowitz Social Anxiety Scale (LSAS), introduced by Dr. Michael R. Liebowitz in 1987, is the most widely used measure of social anxiety in research, clinics, and medication studies. The LSAS rates both fear and avoidance across 24 social and performance situations, giving a full picture of the two key sides of SAD. A large study across cultures (N=31,243; PMC, 2019) confirmed that the LSAS has 5 areas: (1) speaking in public, (2) eating/drinking in front of others, (3) standing up for yourself, (4) working/writing while watched, and (5) talking with strangers. All five factors are covered in this test.
The Social Phobia Inventory (SPIN), developed by Connor and colleagues (2000, British Journal of Psychiatry), is a 17-item self-report questionnaire. It measures fear, avoidance, and physical symptoms of social anxiety. In clinical settings, a SPIN score of 19 or above suggests probable SAD.
Answer based on your consistent experience over the past 6 months — the recurring pattern across different social situations, not your best or worst individual experiences.
Never = 0 | Rarely = 1 | Sometimes = 2 | Often = 3 | Always = 4
Total range: 0–60. This is a screening tool. Only a qualified mental health professional can diagnose Social Anxiety Disorder through a comprehensive clinical assessment.
Understanding Your Social Anxiety Test Score
| Score Range | Category | What It Suggests |
|---|---|---|
| 0 – 15 | Low — Few Social Anxiety Indicators | Social anxiety patterns are not significantly present. Normal social discomfort may be present without a pattern consistent with Social Anxiety Disorder. |
| 16 – 30 | Mild — Some Social Anxiety Patterns | Some social anxiety features are present across one or more domains. Consistent with subthreshold SAD or non-generalized social anxiety. Worth professional discussion. |
| 31 – 45 | Moderate — Significant Social Anxiety | Significant social anxiety across multiple domains. Consistent with generalized SAD. Professional evaluation and CBT-based treatment are recommended. |
| 46 – 60 | High — Strong Social Anxiety Indicators | Pervasive and severe social anxiety across most domains. Consistent with severe generalized SAD. Professional evaluation and treatment are urgently recommended. |
Evidence-Based Treatment for Social Anxiety Disorder
SAD responds very well to treatment. Four major international guidelines recommend CBT as the first-line treatment for SAD in adults: NICE (UK, 2024), the American Psychological Association, the World Federation of Societies of Biological Psychiatry (WFSBP), and the British Association for Psychopharmacology.
Cognitive Behavioral Therapy (CBT) — gold standard. CBT for SAD usually takes 12–16 weekly sessions and follows the Clark-Wells model. It works on the inward focus and safety behaviors that keep the anxiety going. Video feedback helps correct a skewed self-image, since people often believe they look far more anxious than they do. Small real-life tests check specific predictions about what will go wrong. And step-by-step exposure to feared situations, without safety behaviors, builds confidence. The effects are large and last over the long term (Clark et al., 1999, 2001; Liebowitz et al., 2002).
Pharmacotherapy — SSRIs and SNRIs. First-line medications: sertraline, paroxetine, escitalopram (SSRIs), and venlafaxine (SNRI) all have strong evidence for SAD. MAOIs (phenelzine) have the longest evidence history but are rarely first-line due to dietary restrictions. Benzodiazepines provide short-term relief but are not recommended long-term due to dependence risk and interference with the extinction learning that CBT produces. Beta-blockers (propranolol) are sometimes used for the “performance only” specifier — reducing the physiological symptoms in specific performance contexts without treating the underlying disorder.
Group CBT. Group CBT works well for SAD because the group itself is practice. Talking with other members while watching yourself less and using fewer safety behaviors is healing in itself. Group CBT is widely available and often easier to get than one-on-one therapy.
NICE-endorsed stepped care. NICE (2024) recommends a step-by-step approach:
- Learning about SAD and using self-help resources.
- Light-touch guided self-help (CBT workbooks or online CBT with support).
- CBT, one-on-one or in a group program.
- CBT plus medication for complex cases or when other treatment hasn’t worked.
Frequently Asked Questions
What is Social Anxiety Disorder?
Social Anxiety Disorder (SAD; DSM-5-TR 300.23 / F40.10) is an anxiety disorder. It involves strong, lasting fear of social or performance situations where others might watch and judge you. All of the following must be present: marked fear in social situations (Criterion A); fear of negative evaluation (B); almost always provoked (C); active avoidance or endurance with intense distress (D); disproportionate fear (E); duration 6+ months (F); significant distress or impairment (G). SAD is the third most common mental health disorder worldwide, affecting approximately 15 million US adults (7.1%). Onset is typically around age 13. CBT is the gold-standard treatment (NICE 2024; APA; WFSBP).
What is the difference between social anxiety and shyness?
Shyness is a personality trait: a tendency to hold back in new or unfamiliar settings, without real harm to daily life. Most shy people get along fine and feel at ease with people they know. They don’t have the constant dread, inward focus, physical symptoms, and avoidance of SAD. Social Anxiety Disorder involves all of these: strong, lasting fear of being judged across social situations, with avoidance that limits daily life, for at least 6 months. Many people with SAD are not shy in the traditional sense — they may appear socially competent while experiencing significant internal distress.
The difference matters because shyness doesn’t need treatment. SAD does, and it responds well to it.
What are the most common situations feared in social anxiety?
The 5 areas of the LSAS (PMC, 2019) are: (1) speaking or performing in public; (2) eating or drinking in front of others; (3) standing up for yourself (disagreeing, complaining, returning items); (4) working or writing while being watched; and (5) talking with strangers.
Other commonly feared situations include starting or keeping up conversations, meeting new people, going to parties, being the center of attention, speaking up in meetings or classes, using public restrooms when others are there, phoning strangers, dating, and disagreeing with others. The “performance only” DSM-5-TR specifier applies when the fear is only about speaking or performing in public, not everyday social contact.
Is social anxiety disorder treatable?
Yes. SAD is one of the most treatable anxiety disorders. CBT built for SAD helps 70–80% of people in clinical trials, with large effects that last. The Clark-Wells CBT approach is the best-tested talk therapy. It uses video feedback, attention training, small real-life tests that drop safety behaviors, and step-by-step exposure. SSRIs and SNRIs (sertraline, paroxetine, escitalopram, venlafaxine) are effective first-line medications. CBT plus medication is recommended for severe cases (NICE 2024). The biggest barrier is the average 10-year delay in seeking help. Most people with SAD think it is just their personality, not a treatable condition.
What is the LSAS?
The Liebowitz Social Anxiety Scale (LSAS) was introduced by Dr. Michael R. Liebowitz in 1987. It is the most widely used measure of social anxiety in research, clinics, and medication studies. The LSAS rates both fear and avoidance across 24 social and performance situations (maximum total score: 144). In clinical screening research, scores of 30 or more suggested social anxiety disorder and 60 or more the generalized subtype (Mennin et al., 2002). Those cut-offs come from the clinician-administered scale, so treat them only as a rough guide here. A large study across cultures, with 31,243 participants, confirmed the LSAS’s 5 areas: speaking in public, eating/drinking in front of others, standing up for yourself, working/writing while watched, and talking with strangers (PMC, 2019).
What is the difference between social anxiety and agoraphobia?
Social Anxiety Disorder and agoraphobia both involve fear of certain public situations and can lead to similar avoidance. The key difference is the core fear. In SAD, the fear is of being judged, embarrassed, or humiliated by others. In agoraphobia, the fear is of being somewhere that’s hard to escape or where help isn’t available: of being trapped or helpless, not judged. In agoraphobia, having a trusted person along often makes it possible to face avoided places. That isn’t necessarily true in SAD. The Agoraphobia Test covers the agoraphobia presentation specifically.
How does social anxiety relate to avoidant personality disorder?
SAD and Avoidant Personality Disorder (AVPD) share the same core fear, of being judged and rejected, and lead to very similar avoidance. The main differences: SAD is an anxiety disorder. It comes and goes, is tied to certain situations, and usually responds to CBT in 12–16 sessions. AVPD is a personality disorder. It has been present everywhere since early adulthood, is part of a person’s identity, and needs longer therapy.
They often occur together, with estimates from 25–89% depending on the criteria. When both are present, treatment usually tackles SAD first (with CBT), then the wider AVPD patterns (with Schema Therapy or psychodynamic therapy). The Avoidant Personality Disorder Test specifically covers the AVPD presentation.
Related Tests
- Anxiety Test — generalized anxiety disorder and social anxiety frequently co-occur; GAD involves worry across multiple life domains, not specifically social evaluation
- Avoidant Personality Disorder Test — the most important companion test; AVPD shares SAD’s fear of being judged, but as a lasting personality pattern from early adulthood
- Agoraphobia Test — agoraphobia and SAD both produce public-situation avoidance through fundamentally different fear mechanisms; important differential
- Scopophobia Test — fear of being watched or stared at specifically; can exist independently or as part of broader social anxiety
- Clinical Depression Test — depression is the most common social anxiety comorbidity; the social isolation and functional impairment of SAD frequently produce depressive episodes over time
- Burnout Test — the chronic effort required to manage and mask social anxiety in daily life is depleting; burnout and social anxiety frequently co-occur
- Imposter Syndrome Test — imposter syndrome and social anxiety share the fear of being exposed as not good enough; they often occur together and feed each other at work
- Schizotypal Personality Disorder Test — in STPD, social anxiety doesn’t ease as people get to know you, and it comes from paranoid fears rather than fear of judgment; worth ruling out if you keep pulling away from people
- PTSD Test — interpersonal trauma can produce social anxiety symptoms; PTSD involving social situations should be distinguished from primary SAD
- NPC Test — conformity and social anxiety frequently co-occur; fear of standing out drives social conformity in anxious individuals
- Schizoid Personality Disorder Test — withdrawal that comes from genuine disinterest in closeness rather than fear of judgment; the key contrast with social anxiety.
References
- American Psychiatric Association. (2022). Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition, Text Revision (DSM-5-TR). Social Anxiety Disorder 300.23 (F40.10). psychiatry.org
- Stein, D.J., Lim, C.C.W., Roest, A.M., et al. (2017). The cross-national epidemiology of social anxiety disorder: Data from the World Mental Health Survey Initiative. Psychological Medicine, 47(14), 2534–2553. doi.org
- Liebowitz, M.R. (1987). Social phobia. Modern Problems of Pharmacopsychiatry, 22, 141–173.
- Connor, K.M., Davidson, J.R., Churchill, L.E., et al. (2000). Psychometric properties of the Social Phobia Inventory (SPIN). British Journal of Psychiatry, 176, 379–386. doi.org
- Clark, D.M., & Wells, A. (1995). A cognitive model of social phobia. In R.G. Heimberg et al. (Eds.), Social Phobia: Diagnosis, Assessment, and Treatment. Guilford Press.
- Osório, F.L., Crippa, J.A.S., Loureiro, S.R., et al. (2019). Psychometric properties of the Liebowitz Social Anxiety Scale in a large cross-cultural Spanish and Portuguese-speaking sample. European Archives of Psychiatry and Clinical Neuroscience. PMC6781681. pmc.ncbi.nlm.nih.gov
- Anxiety and Depression Association of America. (2022). Social Anxiety Disorder. adaa.org
- NICE. (2024). Social anxiety disorder: recognition, assessment and treatment. Clinical guideline. nice.org.uk
- Mennin, D. S., Fresco, D. M., Heimberg, R. G., Schneier, F. R., Davies, S. O., & Liebowitz, M. R. (2002). Screening for social anxiety disorder in the clinical setting: Using the Liebowitz Social Anxiety Scale. Journal of Anxiety Disorders, 16(6), 661-673. https://doi.org/10.1016/S0887-6185(02)00134-2 pubmed.ncbi.nlm.nih.gov
- MSD Manual Professional Edition. (n.d.). Social anxiety disorder. Merck & Co. msdmanuals.com
Related Tests
See All Quiz →


Anxiety and Fear Disorders · Mental Health
Do I have Obsessive-Compulsive Disorder Test (Free OCD Quiz Online)
→
You may also like
See All Quiz →

